
International Journal of Epidemiology And Public Health Research
OPEN ACCESS | Volume 10 - Issue 5 - 2026
ISSN No: 2836-2810 | Journal DOI: 10.61148/2836-2810/IJEPHR


Bretz P*, Mantik D, Lynch R, Lara D, Stiles A, Bretz J, Djordjevic B
Visionary Breast Center, La Quinta, California, USA.
*Corresponding author: Bretz P, La Quinta, California, USA.
Received: September 10, 2026 | Accepted: September 21, 2026 | Published: September 25, 2026
Citation: Bretz P, Mantik D, Lynch R, Lara D, Stiles A, Bretz J, Djordjevic B. (2026) “What in Breast Cancer is so Beautiful it Has to be Right?”. International Journal of Epidemiology and Public Health Research, 10(4); DOI: 10.61148/28362810/IJEPHR/228.
Copyright: © 2026. Bretz P, This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited.
Breast cancer is one of the last things that bring to mind the word beautiful. But what if there was something beautiful about breast cancer missing from the equation of diagnosis and treatment for all this time? What if there was a way to diagnose nascent tumors before they attainted the capacity to metastasize, kill it in-office in 20 minutes (no huge cancer center needed) with the patient fully awake with her significant other by her side, and normal activity is resumed immediately? It was all accomplished for $2,500.00.
The United States Preventive Services Task Force (USPSTF) saw fit years ago to decree that women in the US need not start mammography until age 50, and only recently lowered it to 40 but still biennial. Medicare and insurance companies take these pronouncements as gospel so obtaining a mammogram outside these parameters is very difficult. How dare they make these decrees implying a correct blanket statement for all women.
A case in point is the prestigious group, The American College of Surgeons Oncology Group, published a paper in 2009 which at the time was the largest study of outcomes in breast cancer for African American women. One of the main conclusions was that these women get breast cancer much earlier (in their 30s) and it’s much more aggressive (triple negative). Does anyone care?
To think for one second that blanket statements can be made in such a complex disease as breast cancer and apply those statements to all women is ludicrous, shameful and as it turns out extremely harmful. An individual surveillance plan is needed.
So, what’s beautiful about breast cancer? Here, diagnosing nascent tumors, killing it in-office with the patient awake, the breast looking untouched with normal activity resumed immediately, no surgery. no chemotherapy no radiation. Lavender is being actively suppressed.
Breast cancer
First, for those who have delved in depth into the structure of the cell, you may recognize that the quote, “It’s so beautiful it has to be right” is a direct quote from Frances Crick when he and James Watson realized they had elucidated the DNA Double Helix. It was put forth in a hand- written letter to his son. What in breast cancer could be so beautiful it has to be right? Let’s just say it: The Lavender Way - Why?
How about being able to consistently diagnose nascent breast cancers before they have the capacity to metastasize and, in the end, leaving the breast basically untouched! Having diagnosed a nascent cancer, would it not be beautiful if you could successfully treat it without surgery, no chemotherapy, no radiation, and no hospital, in 20 minutes all for $2.500.00? Not only that, but the treatment is all in-office with the patient fully awake, and her significant other is allowed in the procedure room to videotape the entire procedure or simply hold her hand.
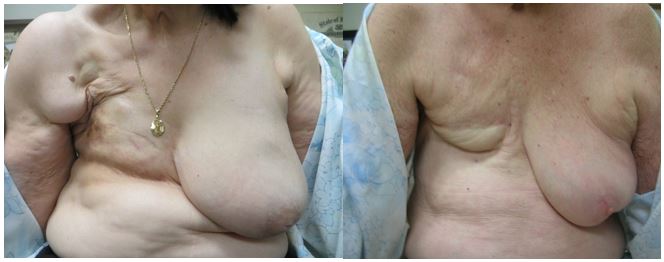
Fig 1 Fig 2
But the act of both of them seeing the cancer being killed in real time on the ultrasound monitor is transformational. It eliminates fear, anxiety, despair, depression and ends the unending sense of futility long term. Why? Because the breast remains intact and she knows the cancer is dead. That is, she can look in the mirror ten days or ten years after and she has no loss of femininity. And unlike the mystery surrounding the standard-of-care surgery in a hospital where everything is a mystery and no one knows what goes on in the operating room, with Lavender it’s the antithesis. Everyone knows what is going on, including seeing the cancer being killed right before their eyes. In reality, it’s impossible to tell if there was any work done at all. There is no peau d’ orange or breast shrinkage associated with six weeks of standard external bean radiation, no perpetual disfigurement. Normal activity is resumed immediately. One patient felt so good that she played 18 holes of golf right after. Many of the other patients chose to go to Lavender Bistro to celebrate, thus the namesake.
Having been trained in the 1970s when aggressive surgery was de rigueur, in the first cryoablation case our surgeon said if this works it will be a “miracle.” It has proved to be just that with 12 years out cancer-free survivors with their breast intact, having had no surgery, no chemotherapy, no radiation, and no hospital and again all for $2,500.00. At this juncture, the reader may wish to visit our website at thelavenderproject.net. Scroll down to the bottom and view some of our videos. Be sure to notice the demeanor of the patients, which is a total reversal of what one habitually sees in the pre-op holding in the hospital where women are scared out of their wits because they really don’t know what’s coming at them next.
To illustrate the point, we present a few of the patients operated on elsewhere that elucidates the problem, and why women are just fed up with all the promises.
Both figures 1&2 show the result of a modified radical mastectomy. And while the surgeon just moves on to the next case, the patient must live the entire rest of her life disfigured with loss of bodily image, not to mention a numb upper inner arm from damage to the first intercostal nerve during the axillary dissection, or a winged scapula if the surgeon bagged the long thoracic nerve. The nerve innervates the serratus anterior muscle which accounts for correct positioning of the scapula. What you see is the reason grandma doesn’t want to leave the house. Oh, but you say, wait a minute, these patients should have had reconstruction. You mean like the ones below?
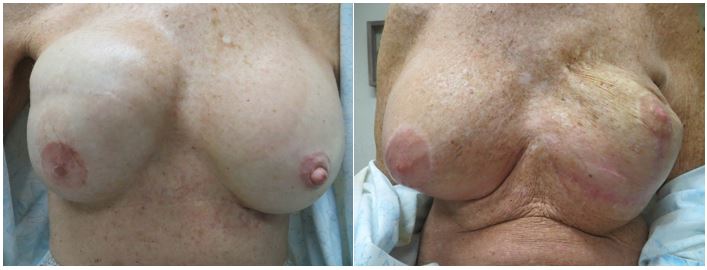
Fig 3 Fig 4
Figure 3 is another state-of-the-art reconstruction including a new nipple. The long scar across the breast doesn’t help. The women should be satisfied you say. Fig 4 is a lady who had a single focus of DCIS and was talked into bilateral subcutaneous mastectomies with immediate reconstruction at a major teaching hospital on the West Coast.
At the time of this photo, she was on her third surgery to correct the obvious problem. But you say wait, you are only showing botched surgeries, there are many great results out there. Don’t deny that. But we say why even have to do reconstruction in the first place! Why have to operate in the first place? Why chemotherapy in the first place? Why radiation in the first place? When there is a viable alternative that should be put to definite large-scale clinical trials, that the medical-industrial complex not only ignores but does everything in its power to not let it see the light of day. G-d forbid the women of America should find out about techniques such as Lavender that might bring down the house of cards.
Of course, the breast cancer cabal, including all the major cancer centers, don’t want to be displaced. Techniques such as Lavender are extremely disruptive to individuals’ jobs and positions of power. What if all the women (and men for that matter) knew that much less invasive techniques like Lavender were being intentionally kept concealed? If they are not, then why is it that a definitive large-scale clinical trial is not on the books (and never will be)? There are only a few people who could force the needed change. One is the Secretary of HHS in the US, one is the Director of the National Institutes of Health, and, of course, the President himself could make it happen, if he only knew. Let’s recap the objective of how to change Fig 5 into Fig 6.
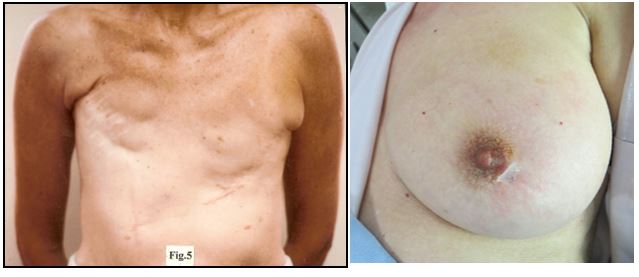
Fig 5 Fig 6
Figure 5 (not ours) shows the results of bilateral mastectomies. A radical on the patient’s right and a modified radical on the left. If you look closely on the right, the surgeon sutured her up like a football. You can tell it’s a radical because just the skin is directly lying over the ribs. In Fig 6, this photo was taken about two minutes after completing the Lavender Procedure, cryoablation using liquid nitrogen. A small dab of antibiotic ointment was always placed over the probe entrance site, never any sutures. In this age of transparency, this patient had a local recurrence about four years later and elected to undergo cryoablation again. She is now 12 years out and her 2026 mammogram was negative for cancer. You say with a local recurrence she should have been submitted to a lumpectomy and post-op radiation.
This shows lack of understanding of the entire dynamic of how we monitor patients post procedure. They are monitored so closely as to find any recurrence while it is still contained and just freeze it again. If we were wrong, then this patient should have had another recurrence and possibly be dead because of it. But no, she is enjoying life with her breast intact in the South of France where she and her husband go every year. This is how we envisioned the patient’s life after Lavender. Need further convincing that STANDARD-OF-CARE IN BREAST CANCER NEEDS A COMPLETE OVERHAUL? Consider the following women.
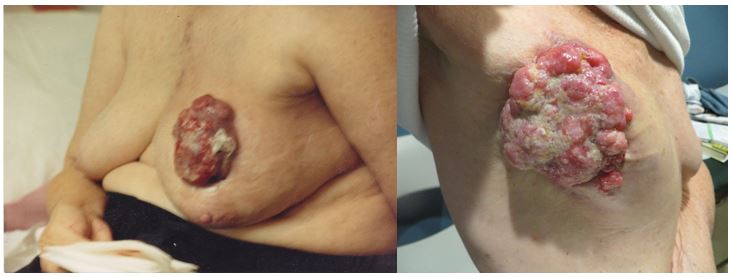
Fig 7 Fig 8
There are a burgeoning number of women who are so afraid of what will happen to them if something is found on the mammogram that they let the tumor just grow out of the skin. We could put up a few more images like these, but the point should be well taken. The point is that we should not be able to see patients like these in the United States, but apparently, we do. Fig 7 shows cancer growing out of the skin. She hid this from her husband for three years. Fig 8 shows a patient who let her cancer grow out of her skin for seven years. It smells, bleeds and chunks of it fall off every day. But she won’t come in for STANDARD-OF-CARE because she is afraid of what will happen to her. Hard to believe but true. Dr. Gupta introduced a new term a few years ago that he called, “time toxicity.’ (1) It means that for some women just the act of picking up the phone to call to make an appointment for a mammogram is so painful and anxiety driven that they elect to do nothing.
An entity called MedStar Health (2) conducted a survey in 2025. They found for women over 40, that 59% were not going to adhere to recommended mammographic guidelines and 23% said they never had a mammogram and they probably weren’t going to get one. What is the system doing for these women who increasingly are fed up with the GAME CHANGER promises they see in the news but get the same old same old slash-poison-burn approach that disfigures them, drains them emotionally, and, for some financial ruin.
The slash-poison-burn approach is taken from a book, “The First Cell,” written by Azra Raza, MD. She holds a chain in oncology at Columbia University in New York. (3) In fact, here is the direct quote:
“With minor variations, a protocol of surgery, chemotherapy and radiation-the slash-poison-burn approach to treating cancer – remains unchanged. It is an embarrassment. Equally embarrassing is the arrogant denial of that embarrassment.”
But you say Fig 7 and Fig 8 are just antidotal cases, and those women had every opportunity to get the appropriate help; they got what they deserved. Really? How is it that we have more to share in America. We could show more but that should be unnecessary.
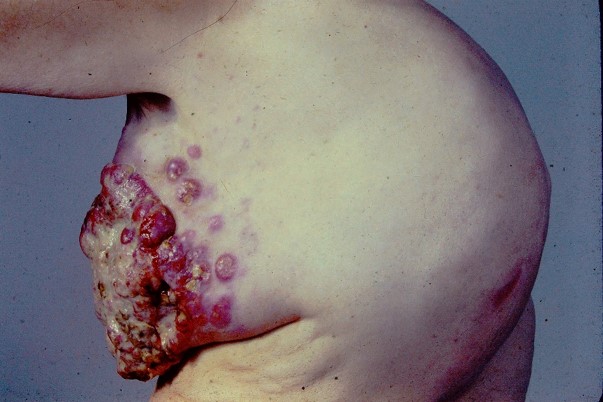
Fig 9
We only saw a minute fraction of the women in the US. But if we picked up so many, there must be thousands out there of the 150 million women. It is inexcusable for the system to not care enough to change the entire dynamic. For those interested in knowing more, please visit our website at thelavenderproject.net. Some of our published papers are there to download under research. And also, please scroll to the bottom to see some of our videos. As you watch, take care to note the demeanor of the patients. Especially pay attention to the patient coming in for her Lavender Procedure dressed in lavender with lavender nails and ring. She says upon entering the procedure room, “I’m ready for the party” with a smile on her face. That’s in direct contrast to the anxiety creating pre-op holding in the cold hospital.
It’s like the system says to ALL women, we know what’s best for you so just suck it up and shut up. Of course, they don’t say that but it’s implied. How do we change this dynamic?
First, we have cared for over 14,000 women from all over the globe for 30 years. While we didn’t learn everything there is to know about women, we know what works and what doesn’t. What works initially is do away with the cold sterile waiting rooms and the phone tree they are forced to put up with. They should have immediate access to their doctor, who they feel comfortable with because they have seen the same doctor for years, some for decades. We created a reception area akin to a well-appointed living room. It’s inviting, not threatening. They get to see their mammogram and ask questions on that visit so there is no anxiety waiting two or more weeks for the result. Both the radiologist and surgeon discuss the mammogram learning from each other because they will know the result of whatever path is chosen for treatment, that’s how experience develops. Don’t take our word for our reception area, below is a handwritten letter from a patient.
While we’re at it, here are a couple more of the hundreds we have received. These are not included to be self-aggrandizing but to make the point that how many letters as a surgeon or mammography center do you receive that are not just Hallmark cards, but patients took the time to write in some cases a lengthy note.
It was letters like this that we knew we were on the right tract to making women feel part of the process that preserved mind, body, and spirit. We just refined it over the years so that we surmounted one of the problems in mammography that is, how to make women want to come in year after year. The next letter took some time to write. And again, it’s not included to be self-aggrandizing. Our notebook is almost three inches thick with these letters. That’s how you keep women coming in and that’s how you save breasts and lives.
At a time when 75% of the physicians in the US are essentially hourly employees “owned” by either the hospital, HMO or private equity firm where seeing the same doctor (you see a real experienced doctor if you’re lucky) to build a meaningful trusting relationship is not a priority, those two letters exemplify the Lavender approach.
In closing, what is it that the Lavender Way incorporates that permits the routine finding of nascent tumors that can be submitted to cryoablation successfully? First, IT’S ALL INDIVIDULAZING MONITORING. Every woman is different and the frequency of imaging is different. Any guidelines for the masses is out the window. When you have entities like the United States Prevention Services Task Force making decrees that Medicare and insurance companies follow making any requests for additional imaging almost impossible because of GATEKEEPERS. Consider a case in point. In 2009 the American College of Surgeons Oncology Group published a seminal paper on African American women and breast cancer (7). One of the conclusions was that this group should begin imaging in their 30s because they were getting breast cancer much earlier and it was more aggressive (triple negative). How does that legitimately compare with the decree of the USPSTF that mammography should not begin until age 50. Age fifty was the target for years and only recently did they say 40. What about girls like Ananda Lewis (an American journalist who had her own TV show on BET) who died at age 51 of metastatic breast cancer, probably because she was afraid to come in for mammography?
We think the edicts of the Lavender Way may well have helped. Then too, there was a former Miss Venezuela who died of metastatic breast cancer at age 26 in a major US cancer center. Lavender may have helped her. In fact, we’ll say that Lavender could help prevent the over 700,000 women worldwide who die yearly of breast cancer, not to mention the over 43,000 who die yearly in the US. Why?
The Lavender Way is made up of several NON-RADIATION DIAGNOSTIC MODALITIES, including a genetics risk test that not only elucidated a woman’s lifetime risk, but when that risk will likely manifest itself within ten years. Here is that list. Mammography is not our main defense; it is secondary as is MRI to the modalities below.
With these modalities in our armamentarium, finding 5mm tumors before they attain the capacity to metastasize becomes axiomatic. It is important to know that while the genetics test determines frequency of imaging most cancers are post-menopausal. If the test is done on a 30 something and she has higher risk after 50, then we have at least two decades to employ preventive intervention, including Tamoxifen or Evista, depending on actual risk.
If we are successful in finding a nascent cancer this then leads the way to The Lavender Procedure, which is cryoablation using liquid nitrogen. The procedure is in-office (no hospital or huge cancer center needed), any trained doctor can do it in the most remote area. That’s why we feel Lavender could be an answer to the worldwide elimination of the suffering wrought by breast cancer. We’re sure the reader realizes our approach is almost the antithesis of standard-of-care in making the diagnosis and treatment. If it’s hard to accept, hopefully one can take a cue from Dante Algiere’s magnificent work, “The Divine Comedy” circa 1320.
In Dante’s Inferno, Virgil takes Dante on a tour of hell among other places. At the entrance to hell is a sign that reads, ALL YEA WHO ENTER HERE ABANDON ALL HOPE. To put that in the context of breast cancer and Lavender, ALL YEA WHO ENTER HERE ABANDON ALL PRECIOUSLY LEARNED DOGMA ABOUT THE DIAGNOSIS AND TREATMENT OF BREAST CANCER. Below now is the genetic test printout.
You can see it looks at the pre-menopause, peri-menopause and post-menopause years. The black bars are the average risk for women. The white bars represent the risk of the patient. This particular patient’s mother died of breast cancer at age 57. This patient went to bed at age 50 thinking if tonight was the night she would wake up with breast cancer. This is a so-called flipper, meaning she is at more risk early on than later. Her mammogram was benign. Below is her infrared exam printout. As you see, it indicates a possible cancer in the right breast UOQ. The following page is that report.
These infrared reports are printed out immediately so the doctor must be fluent in interpretation. It almost always shows the problem, but sometimes it’s like an anagram. The top two images are accompanied by larger or smaller circles, and they are pink, yellow and green that show hot spots or not. In this case, on the left image you can see a larger pink circle in the right breast UOQ. Below on the left are the areas the exam focuses on. In the middle are the bars, dark green, light green, yellow, orange and red.
It’s better to be in the green. The evaluation section next is either low, medium or high. The comment section will identify the quadrant the target is in. The CF bottom right should be at least 2.5 degrees of cooling. The Neural Network contains algorithms that interpret the heat signatures and remember them and compare the patient’s heat signature with the 500 known cancers in the Neural Network. It’s either positive or negative. This report has the pink circle in the right UOQ, a high threshold, a global high reading and a positive Neural Network. While the infrared can’t say it’s cancer, it says the doctor needs to investigate this finding further. We already had a benign reading on mammography, so an MRI was ordered with the results below.
The fact is that infrared picked up the cancer three years before either mammography or MRI called it. One of the failings of infrared is that it can’t as yet actually locate cancer to within 5mm or less, although it can pick up the heat well before neo-angiogenesis. In this patient we had no alternative but to keep ordering mammograms and ultrasounds and three years hence, we found the smallest cancer to date, a 4 mm invasive ductal. Below is the infrared machine, Fig 12 and chair, Fig 11 the patient sits in. The ambient temperature in the room is kept at 73 F. The chair is adjustable and has two first degree mirrors that help image the lateral aspect of the breast. There is no compression or pain as in a mammogram. The machine houses an 8000 BTU air conditioner, two monitors, a printer, and a computer. The exam itself is 4 minutes.
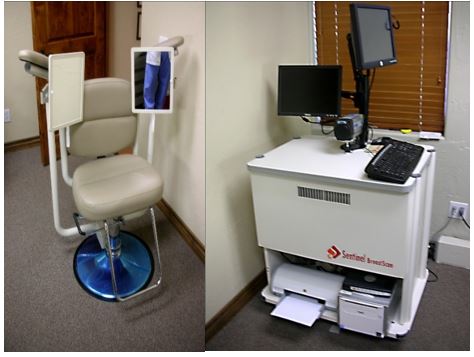
Fig 11 Fig 12
Unlike many infrared studies, there is no need for a cold challenge by the patient putting their hands in ice water. While the infrared machine is FDA cleared, it can’t stand alone, it must be after mammography. I wonder why? Below is the printout of how the pressure sensing device interprets solid from cystic and a single mass from multiple. It is seen in real time just like ultrasound., Fig 13 below.
Let us address one of the complaints the uneducated and recalcitrant have with cryoablation. It is the fact that in performing cryoablation, since we don’t remove the tumor, we won’t know if the margins are clear of cancer or not. While this may seem like a real problem, as none of us want to leave retained cancer at the final pathology margins, it’s not a problem. Here’s why. Before the procedure, the doctor programs the size of the tumor. The computer then tells the doctor where to position the probe for optimal results and the size of the freeze ball. To ensure clear margins (even though we can’t verify under the microscope), we program in the size of the tumor larger than it actually is. For a 1cm tumor, we program at least the size as 1.5cm. This makes it so the freeze ball extends well past the margin of the tumor, as illustrated below.
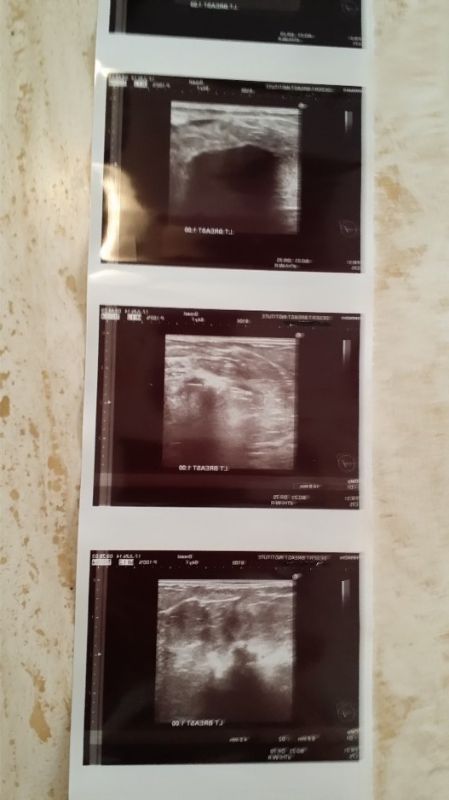
Fig 14
On the bottom is a 5.2mm cancer. In the middle is the cryoprobe going through the tumor. On top is the evolving freeze ball. One can clearly see the freeze ball totally engulfs the tumor by a wide margin. This is why we don’t need to see a pathology report about margins. The results paper is delt with in depth in our other published papers listed in the index.
However, of the patients in groups I and II all are alive 10 years post Lavender having had no surgery, no chemotherapy, no radiation and no hospital. The results paper is delt with in depth in our other published papers listed in the index. However, two patients died. One developed Alsheimer’s and fell getting out of bed hitting her head on the dressed and died before paramedics arrived. She was cancer-free. The other who lived a great distance developed a primary lung cancer, but the breast was clear. Two patients developed local recurrences. One seven years out and again lived a great distance and no one in her local performed cryoablation opted for lumpectomy. She is 12 years out now cancer-free. The other had a local recurrence about 5 years out and had another round of cryoablation. She is 12 years out cancer-free and her 2026 mammogram was negative.
Well, there you have it. If freeing women from this curse without destroying them physically, freeing them from all the psychological side-effects of standard-of-care treatment, and not ruining them financially isn’t wonderous and beautiful, we have different definitions.
One doctor’s office isn’t going to change anything except for our individual patients. The country needs a total re-evaluation of the entire dynamic of how we approach women, how we make the diagnosis, and how we provide the least invasive treatment like Lavender. How can this be accomplished then? The country needs to step up to the plate. We need to develop a NATIONAL BREAST CENTER (see our prior paper We Must Dismantle the Breast Cancer Tower of Babel detailing this), dedicated to preserving mind, body, and spirit. We would need satellite branches, probably at least three or more in each state. We are not advocating the closure of currently running mammogram centers or breast programs. In addition, it’s time for breast fellowship programs to start teaching the surgeons how to put down the scalpel and what it takes to routinely diagnose nascent cancers. One of the fatal flaws of our major cancer centers is they just deal with whatever cancer shows up. There is no finely tuned program in America to discover nascent tumors. The Lavender Way is simply the American way, giving them a choice and let the best man win. We all thought mammography was the answer, it was not.
All this, of course, will require massive expenditure of money. Where could that come from? Besides the government stepping up to the plate and saying to our women, we do actually care about you, and we are going to fix this problem, aren’t there a lot of financially well of individuals who could put their names on buildings? In fact, isn’t there a newly minted trillionaire who could just make it happen by the stroke of his pen? We hate to call him out, but we think breast cancer is one of the biggest issues affecting mankind and more important than going to Mars (at least for now). But yeah, when the time is right, we’d like to go to Mars. Why pinpoint him when there are all these pro athletes making hundreds of millions just for either throwing a ball, hitting a ball or kicking a ball. How many homes, yachts, and Ferraris are enough before they turn their attention to the real needs of mankind?
As always, we stand ready to answer any inquires at phil.bretz@gmail.com.



Open Access By Aditum Open Access Journals id licensed under Creative Commons Attribution 4.0 International License. Based On a Work at aditum.org


