
International Journal of Clinical Case Reports and Medical Cases
OPEN ACCESS | Volume 1 - Issue 1 - 2026
ISSN No: - | Journal DOI: 10.61148/IJCCRM


Emmanuel Ndahiro Manirafasha*, Ngwibete Atenchong, Andrew McLellan, Catherine Uwimana, Helen Ewing
Center for Nursing and Midwifery, University of Global Health Equity, Kigali, Rwanda.
*Corresponding author: Emmanuel Ndahiro Manirafasha, Center for Nursing and Midwifery, University of Global Health Equity, Kigali, Rwanda.
Received: September 20, 2026 | Accepted: September 01, 2026 | Published: October 05, 2026
Citation: Emmanuel Ndahiro Manirafasha, Ngwibete Atenchong, Andrew McLellan, Catherine Uwimana, Helen Ewing., (2026) “Patient Experiences of People-Centered HIV Care in Rwanda: a Cross-Sectional Study” International Journal of Clinical Case Reports and Medical Cases, 1(1); DOI: 10.61148/IJCCRM /004.
Copyright: © 2026 Emmanuel Ndahiro Manirafasha. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited.
Introduction: As HIV has become a chronic condition requiring long-term engagement with health services, attention has increasingly extended beyond biomedical outcomes to how people living with HIV experience their care. In Rwanda, little is known about how people living with HIV experience the people-centredness of routine HIV services.
Methods: We conducted a facility-based cross-sectional survey among 242 adults receiving HIV care at Muhoza Health Center and Biryogo Health Center from May to June 2026. Data were collected using an interviewer-administered electronic questionnaire. Thirty-three items assessed five dimensions drawn from the World Health Organization Integrated People-Centered Health Services framework: empowerment, governance and accountability, model of care, coordination of services, and enabling environment. Items were rated on a five-point scale, with higher scores representing more positive experiences. Data were summarized using frequencies, percentages, means, standard deviations, medians, and ranges.
Results: Participants had a mean age of 39.1 years (SD 11.6), and 187 (77.3%) were women. Only 28 of the 242 participants with valid responses (11.7%) had ever been screened for a mental health condition. Ninety-six participants (39.7%) had not received mental health support but wanted it, while 86 (35.5%) received support sometimes, and 16 (6.6%) received it regularly. The overall composite people-centered care score was 3.81 out of 5 (SD 0.59). The enabling environment received the highest mean score (4.17, SD 0.66), followed by the model of care (3.99, SD 0.61), governance and accountability (3.80, SD 0.90), empowerment (3.68, SD 0.70), and coordination of services (3.05, SD 1.01). Separately, 194 participants (80.2%) reported being satisfied or very satisfied with the overall care received.
Conclusions: Participants generally reported positive experiences of people-centered HIV care, particularly in relation to the enabling environment and model of care. Coordination of services and empowerment were comparatively less positively rated. Differences across participant and service characteristics suggest areas for further investigation and highlight the value of assessing HIV service quality beyond overall satisfaction and biomedical outcomes.
As HIV has become a chronic condition requiring long-term engagement with health services, attention has increasingly extended beyond treatment access and biomedical outcomes to how people living with HIV experience their care. People-centered care emphasizes respect for individuals' values, preferences, experiences, and needs and includes communication, confidentiality, involvement in decision-making, continuity, and responsiveness to psychosocial needs [1]. Mental health and human immunodeficiency virus (HIV) remain closely interconnected public health challenges, particularly in sub-Saharan Africa (SSA), where both conditions are prevalent and highly stigmatized [1,2]. Globally, more than 40.8 million people are living with HIV, with the majority residing in low- and middle-income countries (LMICs).[3] Although advances in antiretroviral therapy (ART) have substantially reduced HIV-related morbidity and mortality, mental health conditions continue to affect the health and well-being of people living with HIV (PLHIV) [4]. Mental health symptoms have been reported in up to 62% of PLHIV [5], while depression occurs at considerably higher rates among PLHIV than in the general population.[6,7] These challenges can affect treatment engagement, adherence, quality of life, and overall well-being.
People-centered approaches have been associated with improved ART adherence, reduced psychological distress, and stronger patient-provider relationships.[8] However, delivering people-centered HIV care remains challenging in many LMICs because limited human resources, fragmented services, weak referral systems, stigma, and resource constraints can affect continuity, confidentiality, coordination, and responsiveness.[9] Mental health and psychosocial support represent one important component of this broader care experience. [10,11] In Rwanda, mental health conditions affect approximately 20.49% of the general population[12], while 16.4% of PLHIV have been reported to experience at least one mental health disorder.[13] Rwanda has made substantial progress in HIV care through expanded ART coverage, decentralized HIV services, and strengthened treatment delivery. Mental health has also been recognized within national HIV guidelines as an important component of comprehensive HIV care.[14] Despite these advances, PLHIV continue to experience depression, psychological distress, stigma, and other mental health challenges, suggesting that expanding access alone may not fully address their mental health and psychosocial needs.[15]
Despite Rwanda's substantial progress in HIV service delivery, limited empirical evidence describes how people living with HIV experience the different dimensions of people-centered care in routine HIV services. Overall satisfaction alone may obscure important differences in experiences of communication, involvement in care, continuity, coordination, accessibility, and responsiveness to psychosocial needs. Understanding these experiences and how they vary across patient and service characteristics can help identify aspects of HIV service delivery requiring further attention. Therefore, this study aimed to assess overall and dimension-specific patient-reported experiences of people-centered HIV care among adults receiving HIV services at two health centers in Rwanda and to describe how these scores varied across selected sociodemographic, HIV-related, clinical, and psychosocial characteristics.
Material and Methods
Study design and setting
We conducted a facility-based quantitative cross-sectional study at Muhoza Health Center and Biryogo Health Center in Rwanda. Muhoza Health Center is located in a semi-urban area of Musanze District in the Northern Province, while Biryogo Health Center serves an urban population in Nyarugenge District, Kigali City. Both facilities provide routine HIV care, including antiretroviral therapy, clinical monitoring, counseling, and referral services. Data were collected from May to June 2026.
Study population and eligibility
The study population consisted of adults living with HIV who were receiving care at either of the two facilities. Participants were eligible if they were aged 18 years or older, had received HIV care at the selected facility for at least six months, were medically stable at the time of recruitment, and were willing and able to provide written informed consent. Clients requiring urgent medical attention or those with severe cognitive or communication difficulties that prevented them from understanding the consent process or completing the questionnaire were excluded. Interviews were paused or discontinued if a participant experienced emotional distress.
Sample size and sampling
The accessible population was estimated at 4,760 people living with HIV, including 1,560 receiving care at Muhoza Health Center and 3,200 at Biryogo Health Center. The overall recruitment target was determined using a finite population formula for estimating a single proportion. Because there was limited prior evidence on patient-reported people-centered HIV care in Rwanda, an expected proportion of 50% was used as a conservative assumption. Using a 95% confidence level and a margin of error of 6.14%, the required sample size was 242 participants.
NZ2p(1-p)d2N-1+Z2p(1-p)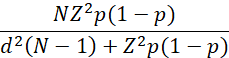
Where:
n = required sample size
N = accessible population size (4,760)
Z = standard normal value corresponding to a 95% confidence level (1.96)
p = estimated proportion of client satisfaction (0.50)
d = margin of error (0.0614)
A proportion of 50% was used because there was limited previous evidence on patient experiences of people-centered HIV care in Rwanda. This value also provides a conservative estimate of the required sample size.
Substituting the values into the formula:
4760(1.96)20.50(1-0.50)(0.0614)24760-1+(1.96)2 (0.5)(0.5)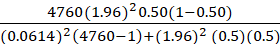 =242 participants
The two health centers were purposively selected. Within each facility, eligible participants were selected from HIV clinic registers or appointment lists using computer-generated random numbers. Selected clients were approached during routine clinic visits and invited to participate. The final sample included 109 participants from Muhoza Health Center and 133 from Biryogo Health Center as it is shown in table 1.
Table 1: Distribution of the study sample by health facility
|
Health facility |
Estimated number of PLHIV |
Final sample size |
Percentage of sample |
|
Muhoza Health Center, Musanze District |
1,560 |
109 |
45.0% |
|
Biryogo Health Center, Kigali City |
3,200 |
133 |
55.0% |
|
Total |
4,760 |
242 |
100% |
Data collection
Data were collected using a structured electronic questionnaire developed for this study and informed by the World Health Organization Framework on Integrated People-Centered Health Services (IPCHS). The questionnaire was available in English and Kinyarwanda and was administered electronically through KoboToolbox by seven trained data collectors. Before data collection, the data collectors received training on the study objectives, eligibility assessment, informed consent, confidentiality, participant safety, and the questionnaire. Interviews were conducted in private areas within the health facilities.
Study measures
Patient-reported perceptions of people-centered care were assessed using 33 items organized according to the five strategies of the WHO IPCHS framework: empowerment, governance and accountability, model of care, coordination of services, and enabling environment. The items addressed participants’ perceptions of routine HIV care, including communication, involvement in care, respect, accessibility, continuity, psychosocial support, and coordination of services. Each item was rated on a five-point scale ranging from 1 (“very dissatisfied”) to 5 (“very satisfied”). An overall composite people-centered care score was calculated as the mean of the 33 items, with a possible range from 1 to 5. Separate mean scores were also calculated for each of the five dimensions, with higher scores indicating more positive perceptions of people-centered care. A separate single-item question assessed participants’ overall satisfaction with care received at the facility and was not included in the 33-item composite score. The questionnaire was developed for this study based on the WHO IPCHS framework. Its content was reviewed by the research supervisors and individuals with experience in people-centered care to assess the relevance and clarity of the items. The questionnaire was pretested before the main data collection, and unclear wording and questionnaire flow were revised based on the pretest findings. Internal consistency of the 33-item people-centered care scale was assessed using Cronbach’s alpha, which showed high internal consistency (α = 0.91).
Data Analysis
Quantitative data were cleaned, coded, and analyzed using Stata version 17. Data were collected using the Kinyarwanda version of the questionnaire, and variable labels and responses were translated into English using a translation codebook for analysis and reporting. Before analysis, the dataset was examined for missing values, inconsistencies, duplicate records, outliers, and invalid responses. Categorical variables were numerically coded as appropriate.
Patient-reported perceptions of people-centered care were assessed using 33 Likert-scale items scored from 1 to 5, with higher scores indicating more positive perceptions of care. The items were organized according to the five dimensions of the World Health Organization IPCHS framework: empowerment, governance and accountability, model of care, coordination of services, and enabling environment. For each participant, an overall people-centered care composite score was calculated as the mean of the 33 items, resulting in a possible score ranging from 1 to 5. Separate mean scores were also calculated for each of the five dimensions, with higher scores indicating more positive perceptions of people-centered care. The overall composite score was retained as a continuous variable and was not categorized into high or low levels.
Descriptive statistics were used to summarize participant characteristics, service-related variables, and people-centered care measures. Frequencies and percentages were reported for categorical variables. Continuous variables were summarized using means and standard deviations and, where appropriate, medians, minimum values, and maximum values. The separate single-item measure of overall satisfaction with care was summarized using frequencies and percentages and was analyzed separately from the 33-item people-centered care composite score. The overall composite score and five dimension-specific mean scores were used to describe participants’ perceptions of people-centered HIV care.
Mean composite scores were further examined descriptively across selected sociodemographic, HIV-related, mental health service-related, clinical, and psychosocial characteristics, including health facility, age, gender, marital status, education, employment status, residence, duration in HIV care, receipt of mental health support, previous mental health screening, viral load status, chronic disease status, and HIV-related stigma or discrimination. These subgroup comparisons were exploratory and descriptive. No inferential statistical tests were conducted to assess statistical significance; therefore, observed differences were not interpreted as evidence of statistical associations, independent predictors, or causal relationships.
Ethical considerations
Ethical approval was obtained from the University of Global Health Equity Institutional Review Board (reference UGHE-IRB/2025/469; protocol 469). Full-board approval was granted on January 26, 2026, and became effective on January 27, 2026. Administrative permission was obtained from both participating health centers before data collection.
All participants provided written informed consent. Participation was voluntary, and participants could decline to answer any question or withdraw without affecting the services they received. No names or direct personal identifiers were collected. Interviews were conducted privately, and study data were stored securely with access limited to authorized members of the research team. Participants who experienced distress or required additional support were connected to the existing counseling, social work, mental health, or referral services available at the health facility.
Results
Participant characteristics
A total of 242 participants completed the study, giving a response rate of 100%. The mean age of participants was 39.1 years (SD = 11.6), with the largest proportion aged 35-44 years, 96 (39.7%). Most participants were female, 187 (77.3%). Regarding residence, 161 (66.5%) lived in urban areas, while 50 (20.7%) lived in peri-urban areas and 31 (12.8%) lived in rural areas. Most participants had completed primary education, 141 (58.3%), and 158 (65.3%) were unemployed. Table 4 presents the socio-demographic and contextual characteristics of the participants (Table 2).
Table 2. Sociodemographic and HIV care characteristics of participants (N = 242)
|
Characteristic |
Category |
Frequency (n) |
Percentage (%) |
|
Health facility |
Muhoza (Musanze) |
109 |
45.45 |
|
Biryogo (Kigali) |
133 |
54.55 |
|
|
Age group of respondents Mean: 39.1 SD:11.6098 |
18-24 years |
31 |
12.8 |
|
25-34 years |
43 |
17.8 |
|
|
35-44 years |
96 |
39.7 |
|
|
45 years and above |
72 |
29.8 |
|
|
Gender |
Male |
55 |
22.7 |
|
Female |
187 |
77.27 |
|
|
Marital status |
Single |
78 |
32.2 |
|
Married or living with a partner |
89 |
36.8 |
|
|
Divorced or separated |
40 |
16.5 |
|
|
Widowed |
35 |
14.5 |
|
|
Key population group |
A man who has sex with men |
4 |
1.65 |
|
Female sex worker |
30 |
12.40 |
|
|
A person who injects drugs |
4 |
1.65 |
|
|
None of the above |
202 |
83.47 |
|
|
|
Prefer not to say |
2 |
0.83 |
|
Highest level of education completed |
No formal education |
33 |
13.6 |
|
Primary school |
141 |
58.3 |
|
|
Secondary school |
54 |
22.3 |
|
|
Post-secondary |
14 |
5.79 |
|
|
Employment status |
Employed, formal |
12 |
5.0 |
|
Self-employed or informal work |
65 |
26.9 |
|
|
Unemployed |
158 |
65.3 |
|
|
Student |
7 |
2.9 |
|
|
Current residence setting |
Urban |
161 |
66.5 |
|
Peri-urban |
50 |
20.7 |
|
|
Rural |
31 |
12.8 |
Age: mean 39.1 years, SD 11.6. Duration in HIV care: mean 13.8 years, SD 12.1.
Mental health support and clinical characteristics
Overall, access to mental health services appeared limited among participants. Only 28 of the 242 participants (11.6%) reported ever having been screened for a mental health condition, while the vast majority (87.2%) had never been screened. Among the 25 participants who reported a screening result, nearly two-thirds (64.0%) had screened positive for a mental health condition. Encouragingly, among those who provided information about follow-up care after a positive screening result, 11 out of 15 (73.3%) reported receiving mental health support or treatment.
Participants also expressed a considerable unmet need for mental health support within HIV care services. Almost four in ten participants (39.7%) reported that they had not received mental health support but would have liked to receive it. A further 35.5% said they received support occasionally, while only 6.6% reported receiving support on a regular basis. About one in five participants (18.2%) indicated that they had not received mental health support and did not feel they needed it.
With regard to HIV clinical status, most participants reported favorable viral load outcomes. More than half (54.1%) reported having a suppressed viral load, while 18.2% reported an undetectable viral load. However, one in five participants (20.7%) did not know their most recent viral load result, and 7.0% reported an unsuppressed viral load. Nearly one-quarter of participants (24.4%) reported living with another chronic disease in addition to HIV. Among the total sample, 17.8% reported receiving treatment for a chronic condition, whereas 5.8% reported having a chronic condition but not receiving treatment. Experiences of HIV-related stigma and discrimination remained common. More than one-third of participants (37.2%) reported having experienced stigma or discrimination related to their HIV status, highlighting the ongoing psychosocial challenges faced by people living with HIV (Table 3).
Table 3. Mental health service, clinical, and psychosocial characteristics
|
Characteristic |
Category |
n |
% |
|
Mental health support as part of HIV care (N = 242) |
No, and did not need it |
44 |
18.2 |
|
No, but wanted it |
96 |
39.7 |
|
|
Yes, sometimes |
86 |
35.5 |
|
|
Yes, regularly |
16 |
6.6 |
|
|
Ever screened for a mental health condition (n = 242) |
Yes |
28 |
11.6 |
|
No |
211 |
87.2 |
|
|
|
Prefer not to say |
3 |
1.2 |
|
Screening result (n = 25) |
Positive |
16 |
64.0 |
|
Negative |
9 |
36.0 |
|
|
Received support after a positive result (n = 15) |
Yes |
11 |
73.3 |
|
No |
4 |
26.7 |
|
|
Most recent viral load result (N = 242) |
Undetectable |
44 |
18.2 |
|
Suppressed |
131 |
54.1 |
|
|
Unsuppressed |
17 |
7.0 |
|
|
Did not know |
50 |
20.7 |
|
|
Diagnosed with another chronic disease (n = 240) |
Yes |
59 |
24.38 |
|
No |
181 |
74.79 |
|
|
|
I don’t know |
2 |
0.83 |
|
Receiving treatment for chronic disease (n = 242) |
Yes |
43 |
17.77 |
|
No |
14 |
5.79 |
|
|
|
Prefer not to say |
2 |
0.83 |
|
|
Not applicable |
183 |
75.62 |
|
Experienced HIV-related stigma or discrimination (n = 242) |
Yes |
90 |
37.19 |
|
No |
150 |
61.98 |
|
|
|
I don’t know |
2 |
0.83 |
Overall composite people-centered care score
The overall composite mean score was 3.81 out of 5 (SD 0.59). Among the five people-centered care dimensions, the enabling environment received the highest mean score (4.17, SD 0.66), followed by the model of care (3.99, SD 0.61) and governance and accountability (3.80, SD 0.90). Empowerment had a mean score of 3.68 (SD 0.70). Coordination of services received the lowest mean score (3.05, SD 1.01), indicating that coordination was the least positively rated dimension (Table 4).
Table 4. Overall and dimension-specific people-centered care scores (N = 242)
|
Measure |
Mean |
SD |
Minimum |
Maximum |
|
Empowerment |
3.68 |
0.70 |
1.89 |
5.00 |
|
Governance and accountability |
3.80 |
0.90 |
1.25 |
5.00 |
|
Model of care |
3.99 |
0.61 |
2.00 |
5.00 |
|
Coordination of services |
3.05 |
1.01 |
1.00 |
5.00 |
|
Enabling environment |
4.17 |
0.66 |
2.14 |
5.00 |
|
Overall composite score |
3.81 |
0.59 |
2.06 |
5.00 |
Scores ranged from 1 to 5, with higher scores representing more positive experiences.
Descriptive variation in people-centered care scores
Mean composite scores varied across selected participants and service characteristics. Participants from Biryogo Health Center had a higher mean score than those from Muhoza Health Center (3.91 versus 3.69). Urban residents had a mean score of 3.86, compared with 3.54 among rural residents. Participants with no formal education had a lower mean score (3.50) than those who had completed primary education (3.89).
Participants who wanted but had not received mental health support had a mean score of 3.62. This compares with 3.96 among those receiving support sometimes and 3.95 among those receiving it regularly. Participants reporting undetectable or suppressed viral loads had mean scores of 3.89 and 3.87, respectively, compared with 3.64 among both those with unsuppressed viral loads and those who did not know their results. Participants with another chronic disease had a mean score of 3.68, compared with 3.85 among those without another chronic disease.
These comparisons were descriptive and were not tested for statistical significance (Table 5).
Table 5: Mean overall satisfaction score by people-centered care dimensions and selected respondent characteristics, N = 242
|
Variable |
Category |
N |
Mean |
SD |
Median |
Min |
Max |
|
Overall composite satisfaction score |
Total |
242 |
3.81 |
0.59 |
3.77 |
2.06 |
5.00 |
|
Empowerment score |
Total |
242 |
3.68 |
0.70 |
3.67 |
1.89 |
5.00 |
|
Governance score |
Total |
242 |
3.80 |
0.90 |
3.88 |
1.25 |
5.00 |
|
Model of care score |
Total |
242 |
3.99 |
0.61 |
4.00 |
2.00 |
5.00 |
|
Coordination score |
Total |
242 |
3.05 |
1.01 |
3.00 |
1.00 |
5.00 |
|
Enabling environment score |
Total |
242 |
4.17 |
0.66 |
4.14 |
2.14 |
5.00 |
|
Health facility |
Muhoza Health Center, Musanze |
109 |
3.69 |
0.61 |
3.58 |
2.42 |
5.00 |
|
Biryogo Health Center, Kigali |
133 |
3.91 |
0.55 |
3.88 |
2.06 |
5.00 |
|
|
Age group |
18-24 years |
31 |
3.95 |
0.55 |
4.00 |
2.49 |
4.79 |
|
25-34 years |
43 |
3.68 |
0.61 |
3.64 |
2.06 |
4.76 |
|
|
35-44 years |
96 |
3.79 |
0.57 |
3.71 |
2.61 |
5.00 |
|
|
45 years and above |
72 |
3.86 |
0.60 |
3.83 |
2.61 |
5.00 |
|
|
Gender |
Male |
55 |
3.80 |
0.60 |
3.73 |
2.06 |
4.88 |
|
Female |
187 |
3.81 |
0.58 |
3.85 |
2.42 |
5.00 |
|
|
Marital status |
Single |
78 |
3.84 |
0.57 |
3.85 |
2.42 |
4.85 |
|
Married/living with partner |
89 |
3.80 |
0.57 |
3.82 |
2.61 |
5.00 |
|
|
Divorced/separated |
40 |
3.74 |
0.63 |
3.62 |
2.06 |
5.00 |
|
|
Widowed |
35 |
3.83 |
0.63 |
3.64 |
2.61 |
4.97 |
|
|
Education level |
No formal education |
33 |
3.50 |
0.51 |
3.39 |
2.61 |
4.97 |
|
Primary school |
141 |
3.89 |
0.57 |
3.85 |
2.42 |
5.00 |
|
|
Secondary school |
54 |
3.79 |
0.59 |
3.82 |
2.06 |
4.79 |
|
|
Diploma/vocational training |
4 |
3.68 |
0.63 |
3.53 |
3.09 |
4.58 |
|
|
University or higher |
10 |
3.84 |
0.78 |
3.89 |
2.49 |
4.85 |
|
|
Employment status |
Employed, formal |
12 |
3.55 |
0.57 |
3.55 |
2.61 |
4.76 |
|
Self-employed/informal work |
65 |
3.74 |
0.57 |
3.70 |
2.06 |
4.97 |
|
|
Unemployed |
158 |
3.86 |
0.59 |
3.85 |
2.42 |
5.00 |
|
|
Student |
7 |
3.77 |
0.59 |
3.88 |
2.49 |
4.21 |
|
|
Residence setting |
Urban |
161 |
3.86 |
0.53 |
3.82 |
2.49 |
5.00 |
|
Peri-urban |
50 |
3.79 |
0.69 |
3.86 |
2.06 |
4.97 |
|
|
Rural |
31 |
3.54 |
0.63 |
3.52 |
2.61 |
5.00 |
|
|
Duration in HIV care |
1-4 years |
35 |
3.77 |
0.50 |
3.79 |
2.73 |
4.55 |
|
5-9 years |
37 |
3.75 |
0.55 |
3.73 |
2.73 |
4.79 |
|
|
10 years and above |
170 |
3.83 |
0.61 |
3.82 |
2.06 |
5.00 |
|
|
Mental health support/counseling as part of HIV care |
No, and I do not need it |
44 |
3.88 |
0.61 |
3.79 |
2.73 |
5.00 |
|
No, but I would like to |
96 |
3.62 |
0.57 |
3.55 |
2.06 |
4.97 |
|
|
Yes, sometimes |
86 |
3.96 |
0.55 |
3.92 |
2.61 |
5.00 |
|
|
Yes, regularly |
16 |
3.95 |
0.55 |
3.89 |
3.12 |
4.79 |
|
|
Ever screened for a mental health condition |
No |
211 |
3.83 |
0.58 |
3.82 |
2.06 |
5.00 |
|
Yes |
28 |
3.61 |
0.62 |
3.59 |
2.49 |
4.49 |
|
|
I do not know/prefer not to say |
3 |
4.21 |
0.60 |
4.30 |
3.58 |
4.76 |
|
|
Most recent viral load result |
Undetected |
44 |
3.89 |
0.57 |
3.95 |
2.61 |
4.88 |
|
Suppressed |
131 |
3.87 |
0.58 |
3.82 |
2.06 |
5.00 |
|
|
Unsuppressed |
17 |
3.64 |
0.54 |
3.70 |
2.61 |
4.49 |
|
|
I do not know |
50 |
3.64 |
0.61 |
3.53 |
2.42 |
5.00 |
|
|
Ever diagnosed with another chronic disease |
No |
181 |
3.85 |
0.57 |
3.85 |
2.42 |
5.00 |
|
Yes |
59 |
3.68 |
0.61 |
3.58 |
2.06 |
5.00 |
|
|
I do not know |
2 |
3.52 |
1.29 |
3.52 |
2.61 |
4.42 |
|
|
Experienced HIV-related stigma/discrimination |
No |
150 |
3.79 |
0.56 |
3.76 |
2.06 |
5.00 |
|
Yes |
90 |
3.85 |
0.62 |
3.85 |
2.42 |
5.00 |
|
|
I do not know |
2 |
3.21 |
0.26 |
3.21 |
3.03 |
3.39 |
Discussion
This study assessed people-centered care experiences among people living with HIV attending two health centers in Rwanda. Participants reported generally positive experiences, with an overall composite score of 3.81 out of 5, although important differences were observed across the five dimensions of people-centered care. The enabling environment received the highest mean score (4.17), followed by the model of care (3.99), governance and accountability (3.80), empowerment (3.68), and coordination of services (3.05). These findings suggest that positive overall experiences can coexist with important differences in how patients experience specific dimensions of HIV care, particularly coordination and empowerment. The generally positive overall satisfaction observed in this study is consistent with previous studies from HIV care settings in Rwanda and other African countries, where PLHIV have reported favorable experiences when services are accessible, treatment is available, and interactions with healthcare providers are supportive.[16–18] Nevertheless, previous research has also shown that favorable overall satisfaction may coexist with weaknesses in communication, privacy, waiting time, infrastructure, continuity, and organization of services.[19,20] The present findings reinforce the importance of examining satisfaction beyond an overall score because a favorable general experience does not necessarily indicate that every dimension of people-centered HIV care is experienced equally positively.
The enabling environment was the strongest dimension of people-centered care, with a mean score of 4.17. This suggests that participants generally perceived aspects of the care environment, including respect, safety, accessibility, privacy, and provider support, positively. Such an environment is particularly important for PLHIV because stigma, fear of disclosure, and emotional vulnerability may influence their willingness to seek care and discuss personal concerns. Respectful, confidential, and nonjudgmental provider-client relationships have been identified as central components of positive experiences in person-centered HIV care.[8,21] Similarly, in mental health care, clients may be more willing to discuss psychological distress, stigma, family difficulties, and other psychosocial concerns when they perceive the clinical environment as safe and supportive.[22] The relatively high enabling environment score, therefore, represents an important foundation for further strengthening people-centered HIV care.
The model of care also received a relatively high mean score of 3.99, suggesting generally favorable perceptions of how services were organized and delivered. This may be considered within the broader context of Rwanda's progress in decentralizing HIV care and maintaining access to antiretroviral therapy and routine follow-up services.[23] However, a positively experienced model of care does not necessarily mean that all aspects of care are equally well coordinated or responsive to patients' broader needs.
This distinction is particularly evident in the coordination of services, which received the lowest mean score at 3.05. The contrast between the high enabling environment score and lower coordination score suggests that positive interpersonal experiences do not necessarily correspond with equally positive experiences of how services are organized and connected. In other words, clients may therefore feel respected, supported, and welcomed by healthcare providers while still experiencing weaknesses in continuity and coordination across different aspects of their care. People-centered care requires both dimensions. Respectful provider-client relationships are essential, but they must be supported by systems that ensure continuity, service linkage, and coordination according to clients' needs.[24]
Mental health screening and access to support provide one example of patients' experiences with services beyond routine HIV treatment. Only 11.6% of respondents reported ever having been screened for a mental health condition, while 39.7% had not received mental health support but indicated that they would like to receive it. These findings identify mental health support as one area of the broader patient experience that may warrant attention within HIV services. When clients are not routinely screened, psychological or psychosocial problems may remain unidentified, reducing opportunities for counseling, referral, or follow-up. This finding is consistent with evidence from Rwanda indicating that mental health disorders among PLHIV may remain underrecognized and undertreated.[13] It is also consistent with broader evidence from African settings showing that shortages of trained providers, weak referral systems, inadequate follow-up, stigma, and other health-system limitations can constrain integration of mental health and HIV services.[1,4,25]
These findings reinforce the importance of examining specific dimensions of patient experience rather than relying solely on overall satisfaction. Patients may report positive experiences in some aspects of care while identifying weaknesses in others, particularly where services require coordination across providers or areas of care. Empowerment was another comparatively weaker dimension, with a mean score of 3.68. People-centered care requires clients to have sufficient information, participate in decisions, communicate their preferences, and understand how to navigate available services. This is especially relevant for PLHIV, who may need to understand antiretroviral treatment, viral load results, mental health risks, available psychosocial support, and referral options. Previous research has emphasized communication, shared decision-making, and meaningful patient involvement as important components of person-centered HIV care.[8,21] The comparatively lower empowerment score in this study suggests that strengthening communication and client involvement should accompany improvements in service coordination.
Governance and accountability received a mean score of 3.80. This finding suggests generally favorable experiences but also indicates room for improving mechanisms through which clients can communicate concerns, provide feedback, and participate in service improvement. Within the WHO IPCHS framework, governance and accountability involve ensuring that health services respond to people's needs, protect their rights, and meaningfully engage individuals and communities in decisions affecting their care.[24] These principles are particularly relevant in HIV and mental health services, where confidentiality and trust can influence willingness to disclose concerns and seek support. Beyond the dimension-specific findings, mean person centered care scores varied descriptively across several sociodemographic, service-related, clinical, and psychosocial characteristics. These patterns should be interpreted cautiously because no inferential statistical tests were conducted. Therefore, they do not establish statistically significant associations, predictors, or causal relationships. Nevertheless, they provide useful indications of groups and service contexts that may merit further investigation.
For example, participants living in urban areas reported a higher mean satisfaction score than those living in rural areas. Previous studies have identified geographical accessibility, transportation, and convenience as factors that can influence experiences of HIV services.[20,26] Although the present study cannot determine why rural participants reported lower mean satisfaction, the pattern highlights the importance of considering accessibility and continuity when designing people-centered services. Similarly, participants with no formal education reported comparatively lower satisfaction. This may indicate a need to ensure that communication and health information are accessible to clients with different literacy levels. People-centered communication should use understandable language, allow sufficient opportunities for questions, and confirm clients' understanding of treatment, mental health information, and referral options.
Mental health support was another important descriptive pattern. Participants who had received mental health support sometimes or regularly generally reported higher mean satisfaction than those who had not received support but wanted it. Although this difference cannot be interpreted as a statistical association, it highlights the potential importance of psychosocial support within the overall care experience. Counseling may provide opportunities for PLHIV to discuss emotional distress, stigma, disclosure concerns, family difficulties, and treatment-related challenges. However, this finding must be considered alongside the very low proportion of participants who had ever received mental health screening. Together, these findings identify mental health screening and support as aspects of the broader care experience that warrant further investigation.
Satisfaction also varied descriptively according to clinical characteristics. Participants with suppressed or undetected viral load results reported higher mean satisfaction than those with unsuppressed or unknown viral load results. This pattern may reflect differences in engagement with care, communication, or reassurance regarding treatment outcomes. Nevertheless, biomedical outcomes should not be used as proxies for people-centered care. Viral suppression and treatment continuity are essential outcomes of HIV care, but they do not fully capture whether clients feel informed, supported, empowered, and able to access appropriate mental health services.[8,21] Similarly, participants with another chronic condition reported comparatively lower satisfaction than those without another chronic condition. Clients managing multiple conditions may require greater coordination across appointments, medications, providers, and referral services, reinforcing the WHO principle that care should be coordinated around people's needs rather than organized solely around individual diseases.[24]
HIV-related stigma also remains relevant to interpreting the findings. More than one-third of participants reported experiencing HIV-related stigma or discrimination, with most reported experiences occurring in the community. Interestingly, those reporting stigma had slightly higher mean satisfaction with services, although this descriptive difference should not be overinterpreted. The slightly higher mean score among participants reporting stigma should not be interpreted as evidence of an association, particularly given the descriptive nature of the analysis. Nevertheless, stigma remains an important psychosocial concern because it can influence emotional well-being, disclosure, social support, and engagement with HIV services [27] Maintaining confidential, respectful, and stigma-sensitive services should therefore remain an important component of people-centered HIV care.
Taken together, the findings highlight an important distinction between overall satisfaction and the multidimensional experience of people-centered HIV care. Although participants generally reported positive experiences, domain-specific scores revealed areas of relative strength and weakness that would not have been apparent from overall satisfaction alone. The findings therefore support assessing HIV service quality not only through biomedical outcomes or global satisfaction measures, but also through patients' experiences of empowerment, governance and accountability, model of care, coordination, and the enabling environment.The principal implication is that efforts to strengthen people-centered HIV care should preserve aspects of care that patients experience positively while addressing comparatively weaker dimensions. Particular attention to coordination, patient empowerment, understandable communication, continuity, and responsiveness to different patient circumstances may improve the overall experience of HIV care. The descriptive differences observed across facility, residence, education, mental health support, viral-load status, and chronic disease also identify areas for further analytical research.
Conclusions
This study found generally positive experiences of people-centered HIV care among adults attending two health centers in Rwanda, although experiences varied across dimensions of care. The enabling environment was rated most positively, while coordination of services and empowerment were comparatively less positively rated. Descriptive differences were also observed across facility, residence, education, mental health support, viral-load status, and chronic disease, although these were not tested for statistical significance. These findings demonstrate the value of examining specific dimensions of patient experience alongside overall satisfaction and biomedical outcomes. Strengthening coordination, patient empowerment, communication, continuity, and responsiveness to different patient circumstances may contribute to more people-centered HIV services in Rwanda.
Competing interests
The authors declare that they have no competing interests.
Authors’ contributions
Emmanuel Ndahiro Manirafasha contributed to the conceptualization and design of the study, data acquisition, data analysis, interpretation of the findings, and preparation of the original manuscript draft. Ngwibete Atenchong, Andrew McLellan, Catherine Uwimana, Helen Ewing, Augustine Ndaimani, and Daniel Maweu contributed substantially to the interpretation of the findings and critically revised the manuscript for important intellectual content. All authors reviewed and approved the final version of the manuscript and agreed to be accountable for all aspects of the work, including ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Acknowledgments
The authors sincerely thank the people living with HIV who participated in this study and shared their experiences. We also acknowledge the leadership and staff of Muhoza Health Center and Biryogo Health Center for supporting the study. We are grateful to the data collectors for their contribution to participant recruitment and data collection.
Funding
This study was funded by the University of Global Health Equity, Center for Nursing and Midwifery.
Data availability
The deidentified data supporting the findings of this study may be obtained from the corresponding author upon reasonable request, subject to relevant ethical and institutional requirements.
List of abbreviations
ART: Antiretroviral therapy
HIV: Human immunodeficiency virus
IPCHS: Integrated People-Centered Health Services
PLHIV: People living with HIV
UGHE: University of Global Health Equity
WHO: World Health Organization.

Open Access By Aditum Open Access Journals id licensed under Creative Commons Attribution 4.0 International License. Based On a Work at aditum.org


